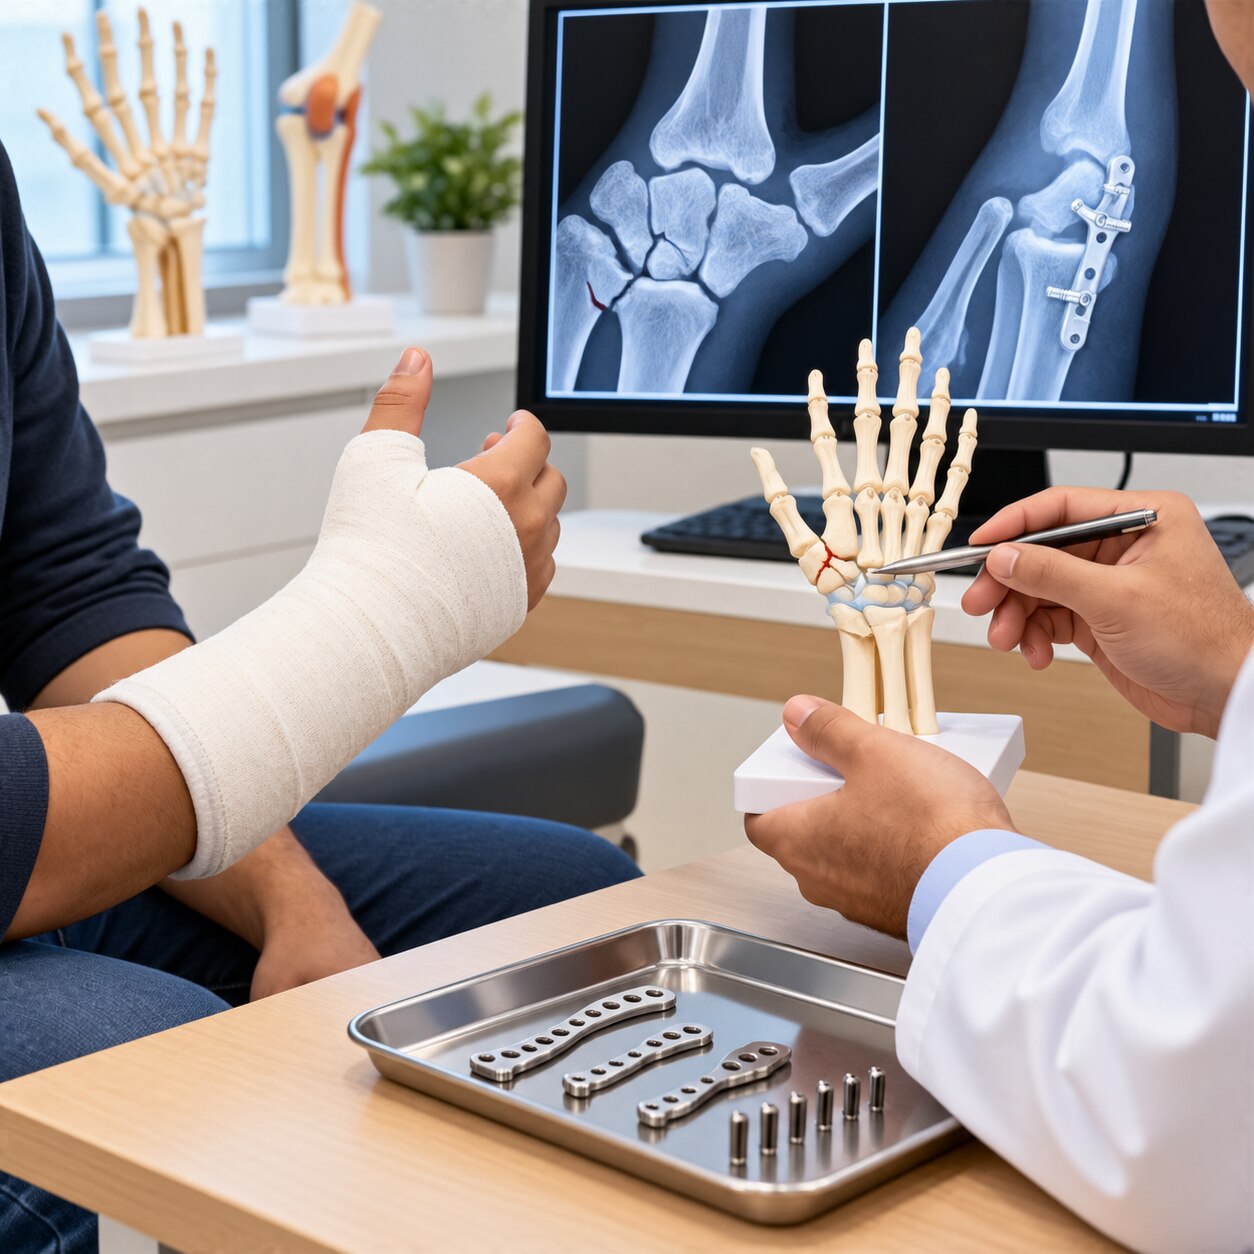
The better treatment depends on whether the thumb-base fracture is stable enough to remain aligned, not on a blanket rule that surgery always wins. By comparing the X-ray and CT findings, fixation choices, cast requirements, risks and follow-up plans, you can ask more precise questions before choosing treatment.
Key takeaways
- Casting fits stable, acceptably aligned fractures without thumb CMC subluxation.
- Repeat X-rays confirm whether alignment holds during early healing.
- Displacement, joint incongruity, or instability can favour fixation.
- Compare surgical risks with stiffness, displacement, and arthritis risks from casting.
Which fracture patterns can be treated with a cast, and which need fixation?
A cast fits a nondisplaced or acceptably aligned Rolando fracture when the joint surface is stable, first-metacarpal length and alignment are preserved, and the thumb CMC joint is not subluxed. Repeat X-rays must show that the fracture remains positioned during early healing.
| Option | Pattern or finding | Usual direction |
|---|---|---|
| Casting | Stable alignment, preserved metacarpal length, congruent CMC joint, no meaningful articular gap | Thumb-spica immobilisation with repeat X-rays |
| Reduction and casting | Alignment is first restored by a closed reduction, then held in a cast | Appropriate only if the reduction remains stable |
| Fixation | Displacement, articular step-off or gap, CMC subluxation or dislocation, shortening, angulation, unstable fragments, or an open fracture | Reduction with K-wires, screws, plates or another fixation method |
| Fixation after casting | Alignment is lost inside the cast or cannot be maintained on follow-up films | Reassessment and operative stabilisation |
Closed reduction followed by casting is not the same as simply applying a cast to an already aligned fracture. A cast can look satisfactory on day one and still fail when swelling falls or deforming forces shift the thumb base.
Seek urgent assessment for an open wound, marked deformity, numbness, a pale or cold thumb, rapidly increasing swelling, or inability to move the thumb. Rolando fracture treatment in Bengaluru should follow the actual fracture pattern, hand function and follow-up reliability—not the label “surgery” or “casting” alone.
Which X-rays and scans show whether the joint can be held in position?
Dedicated thumb and wrist X-rays show whether the fracture is aligned and likely to remain so. Start with anteroposterior, lateral and oblique thumb views, adding wrist views when needed to assess the carpometacarpal (CMC) joint.
Look for:
- First-metacarpal length and overall alignment
- The position and size of each fracture fragment
- Joint-surface gaps or step-off
- CMC-joint subluxation or dislocation
Plain films are the starting point for intra articular thumb fracture treatment. CT becomes useful when overlapping fragments hide the joint surface, the fracture is highly comminuted, or the surgeon needs a three-dimensional map for fixation planning.
| Investigation | What it clarifies | How it can affect treatment |
|---|---|---|
| Thumb and wrist X-rays | Alignment, length, fragments and CMC congruity | Casting or reduction and fixation |
| CT scan | Overlapping fragments and reconstructable joint surface | Percutaneous K-wires, open reduction and internal fixation, limited fixation or external fixation |
| Follow-up X-rays | Whether reduction is maintained as swelling changes | Continue casting or change the plan |
The frequently quoted 1–2 mm articular step-off figures are decision aids, not automatic commands. Fragment size, instability, patient demands and the ability to maintain reduction also matter. Compare every follow-up X-ray with the original films, especially during the first weeks after reduction or casting, when secondary displacement can appear.
What does casting involve, and when is it a reasonable choice?
Casting is reasonable when a reduced Rolando fracture remains acceptably aligned and the CMC joint surface is stable. A thumb-spica cast immobilises the wrist and thumb, usually including the thumb metacarpal and thumb MCP joint, while leaving the fingertips visible for circulation checks. The treating surgeon chooses the exact design according to the reduction.
| Cast treatment | Practical effect |
|---|---|
| Gripping and pinching | Avoid them; they load the fracture |
| Lifting | Do not lift with the injured hand |
| Driving | Avoid driving until cleared |
| Thumb movement | Do not actively move the thumb inside the cast |
For Rolando fracture surgery or casting in Bengaluru, casting is not a low-maintenance option for an unstable injury. Repeat X-rays are needed after swelling changes and during early healing because a cast can lose reduction and allow secondary displacement.
Keep the cast dry and never push objects underneath it. Return promptly for increasing pain, numbness, colour change, swelling, pressure points, or a loose, cracked, wet, or damaged cast.
Casting avoids an incision, implanted hardware and pin-site care. Its trade-offs include loss of reduction, malunion, persistent joint incongruity, stiffness and later post-traumatic arthritis.
Thumb movement and strengthening begin in stages after imaging confirms adequate healing. Starting too soon risks displacement; immobilising too long increases stiffness. Ask how often imaging is required before choosing casting.
What does surgery involve, and what risks should you compare with casting?
Surgery is not one procedure: the choice depends on fragment size, stability, CMC-joint congruity and your ability to complete rehabilitation.
| Option | What it involves | When it applies |
|---|---|---|
| Closed reduction with percutaneous K-wires | Small skin punctures guide wires across aligned fragments; no joint incision | Fragments can be aligned and controlled without opening the joint |
| Open reduction and internal fixation | An incision exposes the joint; plates or screws restore the joint surface directly | Displacement requires direct reduction and stable fixation |
| Limited fixation or external fixation | Selected fragments receive support without reconstructing every piece with a plate | Small or highly comminuted fragments cannot be reliably reconstructed with a plate |
The procedure is scheduled after assessing swelling, skin condition, X-rays and CT findings; open wounds or threatened circulation need urgent treatment. Anaesthesia may be regional or general. Afterward, expect immobilisation, protection from gripping and lifting, wound review, dressing changes and repeat imaging. K-wires also require clean, dry pin-site care and protection until removal.
Movement progresses from protected immobilisation to thumb and wrist therapy when fixation and healing allow it, not simply when pain decreases.
Possible surgical problems include infection, nerve irritation, tendon irritation, stiffness, prominent or failed hardware and repeat surgery. Casting avoids an incision, implants and pin-site care, but an unstable fracture can lose reduction, heal with an incongruent CMC joint and require later surgery.
Thumb base fracture surgery is not automatically superior: the right operation is the one that restores stable alignment without adding avoidable tissue injury.
How should you choose a treatment plan in Bengaluru?
Choose treatment from the images and the joint’s stability, not from clinic location or the label “Rolando fracture.” Ask the surgeon to review your actual thumb and wrist X-rays or CT scans with you.
| Option | What to assess | When it applies |
|---|---|---|
| Casting | Alignment, metacarpal length, joint-surface congruity and stability | A fracture that is acceptably aligned and remains positioned on repeat X-rays |
| Surgery | Reduction, fixation method and ability to restore CMC alignment | Reduction cannot be achieved or maintained, or the joint is subluxed |
| Both | Stiffness, rehabilitation and later arthritis risk | Neither option guarantees a pain-free joint permanently |
Use this consultation checklist:
- Ask the surgeon to point out the articular step-off or gap and explain whether the thumb CMC joint is subluxed.
- Ask why the fracture is expected to hold alignment in a cast, or what force and fragment pattern could make it lose alignment.
- If surgery is recommended, ask whether the plan is percutaneous K-wires, open reduction and internal fixation with screws or a plate, limited fixation, or external fixation.
- Confirm when repeat X-rays will occur, how long the thumb and wrist will remain immobilised, and when thumb motion and hand therapy will begin.
- Ask how a wound or K-wires will be protected and cleaned, and which finding would change casting to surgery.
Choose a hand-and-wrist or upper-limb orthopaedic specialist familiar with intra-articular thumb fractures. A rolando fracture specialist in Bengaluru should connect imaging, CMC stability, fixation choices and rehabilitation; Dr Harish Madrekar's Orthopaedic Clinic is one Bengaluru option for that assessment.
Casting works for a stable, acceptably aligned fracture that remains aligned. Surgery is favoured when reduction cannot be achieved or maintained, but neither choice guarantees freedom from later arthritis.
Related service
FRACTURE SURGERY Rolando Fractur -intra-articular fracture at the base of the first metacarpal Rolando Fracture Surgery A Rolando fracture is a complex, intra-articular fracture at the base of the first metacarpal involving the thumb... View service → |
Frequently asked questions
Which Rolando fractures can be treated with a cast?
A cast can suit a nondisplaced or acceptably aligned fracture when the thumb CMC joint is stable, first-metacarpal length is preserved, and repeat X-rays show maintained position.
Which X-rays or scans help decide between casting and surgery?
Thumb and hand X-rays show displacement, joint-surface incongruity, metacarpal shortening, and CMC subluxation. CT can clarify complex articular fracture fragments when plain X-rays do not show the pattern clearly.
What does Rolando fracture surgery involve?
Fixation restores the thumb metacarpal base and joint alignment using wires, screws, a plate, or a combination selected for the fracture pattern. The surgeon then protects healing with immobilisation and follow-up imaging.
What should you compare before choosing surgery or casting in Bengaluru?
Compare joint alignment, stability, fracture complexity, hand demands, healing follow-up, stiffness risk, infection and nerve risks, and the chance of losing alignment in a cast.
Keywords